What it is
Plenty of EMRs advertise a microphone. In almost all of them, voice is a transcription bolted onto a system that still expects templates, dropdowns, and a separate order screen. You dictate a paragraph, then spend as long fixing the structured fields the paragraph did not fill.
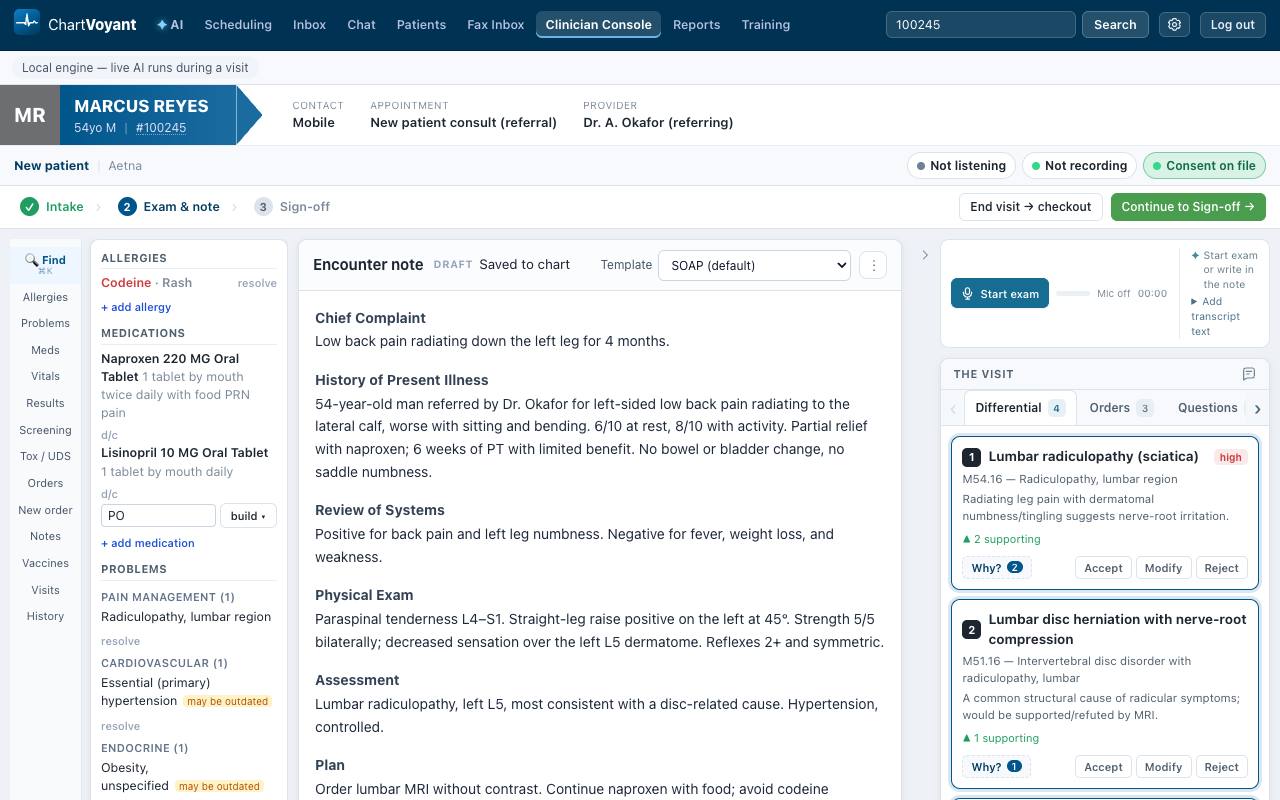
ChartVoyant inverts that. Speech is the primary interface. A clinician in a Cleveland, Tennessee pain clinic talks through history, exam, and plan the way they would explain it to a colleague. The note assembles as they speak. Orders and medications mentioned aloud surface as proposals. Diagnosis and procedure codes take shape from the medical decision making rather than from a coding pass after the patient has left.
On the clinic floor
The visit is three rooms, not twelve tabs. Intake is already on the chart from the desk or the kiosk. Exam & note keeps the document on screen while you talk; Start exam, the microphone, and the note status share one bar; the differential opens beside the note. The chart rail stays editable. Leaving the exam for the note is instant — the note writes into the open page, in clinical language, with the exam card and the orders you entered included.
A spoken order is accepted with one click. Nothing rewrites the note on arrival. End exam no longer clears the AI panel or confirmed orders. That last sentence is not a slogan; it is a specific failure mode the product had, and fixed, because a clinician who loses their confirmed orders once will type them forever after.
What AI does, and what a clinician confirms
The model drafts. It does not sign, place, or transmit. A spoken medication is a proposal. A spoken MRI is a proposal. The recommended E/M level is presented with the decision-making elements behind it, not as a single number to batch-accept. High-stakes actions get their own explicit confirmation and cannot be batched. That is the operational form of Non-Device CDS: the clinician can independently review the basis of every suggestion, and the software does not interpret images or physiologic signals.
Non-Device CDS
ChartVoyant stays outside FDA device regulation by keeping diagnosis and treatment features human-in-the-loop, transparent, and draft-only. There is no autonomous clinical decision. “Streamlining” a confirmation step is not an option we will take.
Where this sits vs bolted-on tools
A standalone ambient scribe that pastes a note back into another EMR is a second application open during the visit. Adoption leaks at every extra window. ChartVoyant’s documentation engine is the chart: the transcript is evidence for the draft, the draft is the note you attest, and the attested note is what billing, prior auth, the after-visit summary, and the portal all read. There is no copy-paste hop, which is also where most PHI leaks in bolted-on scribes.
The honest limit: for an experienced physician with a well-built template on a clean follow-up, typing can still be faster. The case for voice-first is strongest on visits that are conversational, variable, and cognitively loaded — which describes most of ambulatory pain medicine, and not all of it.